Early Dementia Care Choices: Is Memory Care or Assisted Living the Better Fit?
Business Name: BeeHive Homes of Henderson
Address: 1000 Greenway Rd, Henderson, NV 89002
Phone: (702) 551-0265
BeeHive Homes of Henderson
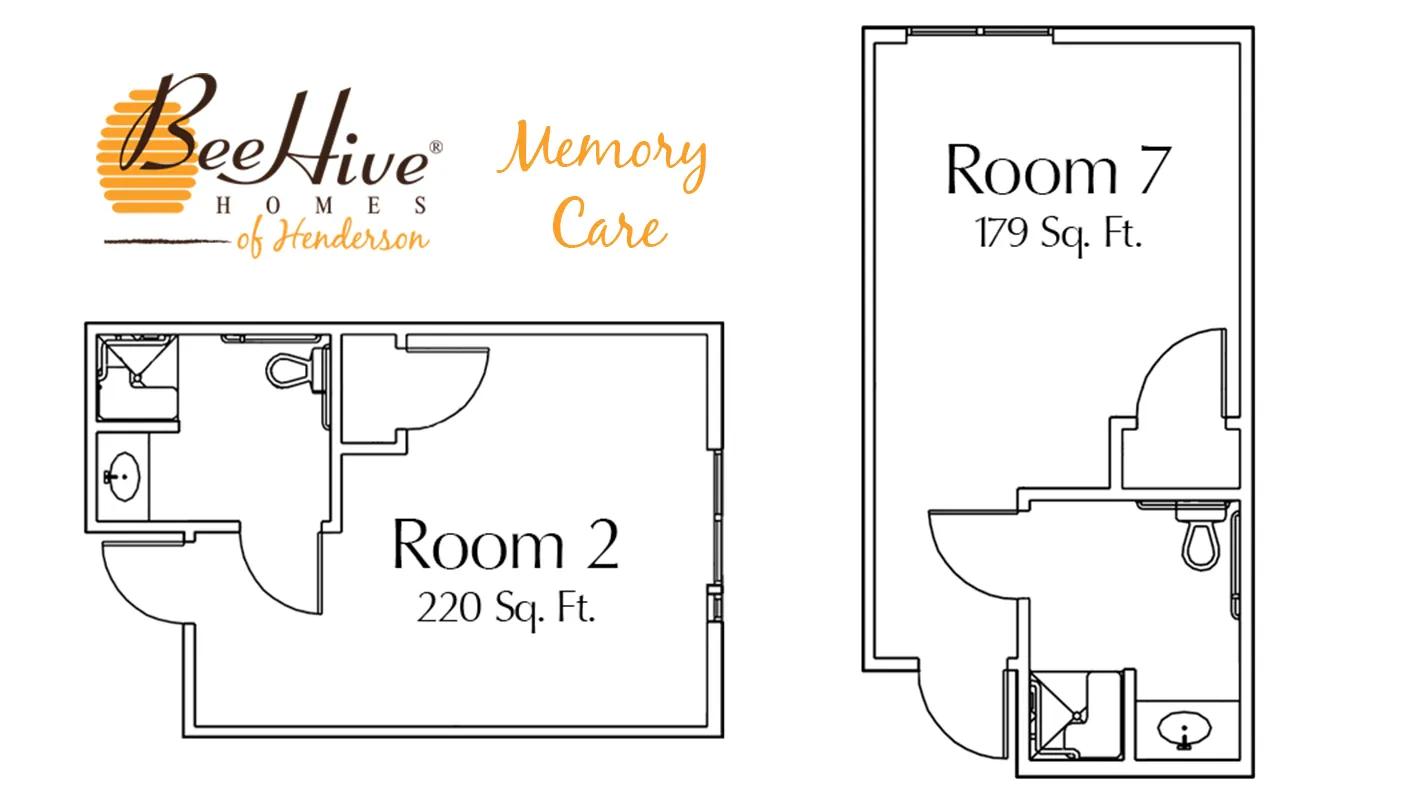
At BeeHive Homes of Henderson, Nevada, we offer the finest assisted living and memory care experience available in a cozy, comfortable homelike setting. Each of our residents has their own spacious room with an ADA approved bathroom and shower. We prepare and serve delicious home-cooked meals three times a day every day. We maintain a small, friendly community of only 20 residents per home. We provide regular activities that our residents find fun and contribute to their health and well-being. Our staff is attentive and caring and provides assistance with daily activities to our residents in a loving and respectful manner. We would like to invite you to tour and experience our memory care & assisted living home and feel the difference.
1000 Greenway Rd, Henderson, NV 89002
Business Hours
Families typically arrive at the very same crossroad: a loved one has received an early dementia medical diagnosis and is starting to lose ground with errands, bills, meals, or medication regimens. Everyone can see that living totally alone has actually ended up being risky. The question that follows is stealthily simple. Should we begin with assisted living, or move directly into a memory care home? The right response depends less on the label and more on your loved one's specific pattern of strengths, risks, and preferences, plus what regional neighborhoods really supply behind their brochures.
I have actually walked this choice with hundreds of families. I have seen dazzling starts in assisted living that extended independence for several years, and I have actually viewed other citizens support just after moving to memory care. The option is part clinical assessment, part household logistics, part gut check about security. There are trade‑offs either way.
What "early dementia" typically looks like
Dementia is an umbrella term explaining progressive cognitive decline that interferes with day-to-day function. Early stages can be subtle. The majority of people still gown and shower independently and hold a significant discussion, particularly in the early morning. The fractures frequently display in what clinicians call important activities of daily living, the complex tasks that keep a home running.
Patterns I typically see include overdue expenses accumulating, repeated online purchases, a fridge loaded with ended food, missed out on medication dosages, and circular driving routes after basic errands. Friends might observe social withdrawal or that stories repeat 3 times over lunch. Short‑term memory slips are the heading, but evaluating threat can be tougher. I once worked with a retired engineer who might describe every bolt on a mower, yet might not remember he had currently taken his blood thinner. The memory failure mattered because of the medication's stakes.
Early symptoms vary by kind of dementia. Alzheimer's alters to memory and word finding. Vascular dementia looks patchier, with good days and bad days, or weak point on one side after duplicated small strokes. Lewy body dementia can present visual misperceptions and big swings in awareness, that makes security unforeseeable. Frontotemporal dementia can show up with changes in judgment and impulse control long previously memory stops working, so an extremely verbal person might sound fine while making dangerous options. These subtleties affect whether an assisted living setting can supply adequate oversight to prevent injuries and elopement, or whether the structure of memory care is the safer foundation from the start.
What assisted living really offers
Strip away the sales language and you will discover that assisted living is developed for individuals who require help with some everyday jobs however do not require 24‑hour scientific guidance. Staff help with bathing, dressing, grooming, toileting, and medication management. Meals are prepared, housekeeping is included, and there are social activities. Many buildings have lovely typical locations, courtyards, and on‑site hair salons. Citizens usually live in private houses, lock their own doors, and come and go to group occasions as they choose.
Staffing in assisted living is variable. A typical daytime pattern is one caregiver for eight to twelve locals, with thinner ratios overnight. Nurses are normally not on website all the time, although some larger neighborhoods have an LPN or registered nurse during service hours, plus on‑call arrangements. Laws differ widely by state. Some states allow assisted living to accept locals with moderate cognitive problems or early dementia if they can do so securely, while others need a move to a secured memory care unit at the first indication of wandering risk. The label does not guarantee capability; inquire about real staffing, training, and resident mix.
From a cost viewpoint, assisted living normally begins with a base regular monthly rate for space and board, then adds a care fee based upon examined needs. In lots of markets, base rates fall in the 3,500 to 6,000 dollars vary for a studio or one‑bedroom, with care fees adding 500 to 2,500 dollars depending on assistance required. Medication administration, incontinence supplies, and escorts to meals often come as different line products. Check out the menu of fees as you would check out an airline's baggage policy, and ask how typically reassessments happen. In a lot of buildings, care levels are examined every 30, 60, or 90 days.
When assisted living works well for early dementia, it is due to the fact that it supplies the right scaffolding without smothering independence. A retired teacher I worked with moved into assisted living when she started burning pots and skipping meals. With 3 ready meals, medication pointers, and a morning hint to shower, she restored weight, rejoined a book club, and stayed 5 years, moving only when roaming began after dusk. She understood her next-door neighbors and made her method with confidence from her apartment or condo to the dining-room. That familiarity had value that no checklist can capture.
What memory care contributes to the equation
Memory care is created for individuals coping with dementia, starting to end. The constructed environment and day-to-day regimens decrease confusion and reduce threats that assisted living can not reliably control. Think of it as assisted living plus dementia‑specific shows and security.
Most memory care homes are secured. Doors require a code to exit, and there are alarms or sensors on perimeters. This does not turn the unit into a prison. Residents go outside into secured yards, participate in monitored neighborhood outings, and keep a daily rhythm. The goal is to prevent hazardous roaming, a threat that increases as soon as someone forgets where they were headed or misjudges traffic. Personnel get specialized training in redirection, acknowledging unmet needs that sustain agitation, and cueing techniques for bathing and dressing. The activity calendar looks various too. Instead of trivia contests covering odd dates, you will see task‑based programs like folding warm towels, baking, gardening, or music that draws on long‑term memory. Montessori‑inspired dementia care, respite care where jobs are streamlined and choice‑driven, has actually ended up being more noticeable in well‑run communities.
A strong memory care program pays attention to sensory load and routine. Lighting follows a consistent day‑night pattern to lower sundowning. Corridors might include shadow boxes with individual mementos outside each room to help with wayfinding. Dining utilizes color contrast on plates and tablecloths to compensate for visual‑perceptual modifications. Speech is brief and concrete. Noise is moderated. Personnel ratios are tighter than in assisted living, sometimes one caretaker to 6 or 8 residents throughout the day, and one to 10 or twelve overnight, though this differs extensively. On‑site nursing hours likewise differ; some memory care systems share a nurse with the assisted living building next door.
Memory care expenses more. In most areas, families ought to anticipate 20 to 30 percent above assisted living rates. A reasonable working range is 5,000 to 9,000 dollars monthly, with higher expenses in seaside cities and lower in backwoods. That boost reflects staffing and programs intensity, secured style, and greater oversight. Some communities bundle care into a flat memory care rate that includes medication administration and incontinence support. Others still use a tiered model. When you tour, ask what activates a cost dive, and what happens if care needs surpass what the unit can safely provide. Every community has a discharge threshold, even if they prevent calling it.
I often fulfill households who stress that memory care will feel infantilizing or too restrictive for someone in the early phase. This is not guaranteed. The best memory care areas build choice into the day, honor adult identities, and resist the impulse to overassist. I have actually seen a former civil engineer continue to manage a communal tool caddy for light jobs, and a retired nurse lead a hydration round. What modifications is the safeguard, not the individual's worth.
Overlap and key differences
Both assisted living and memory care supply meals, housekeeping, social engagement, and assist with personal care. The distinctions show up in what happens when somebody is puzzled or at risk.
Assisted living expects more independent navigation. If your mother can dependably find the dining room, utilize an elevator, and return to her apartment or condo, assisted living keeps her in a familiar, apartment‑style flow. If she gets lost between her door and the lobby, panics when an alarm sounds, or wanders looking for a kid who is now a grown adult, that dynamic overwhelms most assisted living floors. Staff in assisted living are kind and strive, but they are not set as much as monitor exit doors continuously, upgrade an activity for someone who can not follow actions, or pacify late‑day restlessness with structured sensory input.
Memory care anticipates confusion and prepare for it. Redirection is a core skill, not a periodic courtesy. Exit‑seeking is prepared for, and the building works together with the plan rather than counting on personnel to chase alarms. The everyday routine offers clear start and stop cues. When cognition dips in the afternoon, there are much shorter, tactile activities and peaceful spaces that soak up that energy. The whole system is shaped around dementia care.
Medication safety is a strong differentiator. In assisted living, homeowners can often manage their own medications if they demonstrate proficiency, though numerous pick staff administration. In memory care, staff deal with medications as a guideline, which decreases threats of double dosing or avoided tablets that destabilize blood pressure, blood glucose, or mood.
Another line is the action to habits that signify distress. If your father develops fear that products are being taken, or he misreads patterns on a carpet as pests, a memory care team will have training in how to validate the sensation, reduce triggers, and shift jobs with dignity. Assisted living might ask the household to supply private duty hours to cover the gap, or they might suggest a transfer if the pattern persists.
Where starting in assisted living makes sense
If your loved one has early dementia with good insight, no wandering history, and consistent daytime function, assisted living can be a strong initial step. People who grow in assisted living tend to value privacy and the feel of an apartment or condo, prefer a lighter touch from personnel, and delight in a more varied peer group that includes residents without cognitive problems. Some couples pick assisted living so they can share a standard house and routine while just one partner receives assistance, especially when memory care homes in the area are mainly private studios.
Finances can tip the scale too. If the spending plan is tight and the distinction in monthly cost would cut years off cost, beginning in assisted living and planning for a later move might be pragmatic. A veteran's Help and Presence benefit can offset 1,200 to 2,300 dollars monthly, depending upon marital status. Medicaid coverage for assisted living and memory care differs by state and program, and numerous communities keep a minimal variety of Medicaid waiver slots. When funds are finite, ask each structure's director whether residents can convert to Medicaid in location, and if so, for how long the personal pay duration need to be first.
I suggest assisted living when a strong family existence adds oversight. If a child visits 3 times weekly, notices early modifications, and can act quickly to adjust the strategy, assisted living's lighter supervision ends up being less risky.
Where moving directly to memory care is the safer call
Three patterns steer me to memory care from the start. The very first is exit‑seeking or a continual wandering history, even if there was no real elopement. The second is bad safety judgment combined with confabulation, such as turning on the range and forgetting it is hot, insisting on driving after getting lost, or handing out cash to complete strangers by phone. The third is behavioral change that needs constant dementia‑specific methods to prevent escalation, for example late‑day agitation or misinterpreting benign interactions as threats.
Families frequently ask whether starting in assisted living could buy time while preserving self-respect. If any of those patterns exist, you are not trading dignity for security by choosing memory care. You are picking a setting where the walls, staffing plan, and day-to-day rhythm fulfill the person where they are.
Here is a fast filter I share in family meetings.
- Repeated roaming or exit‑seeking in the past 60 days
- Unsafe cooking area or medication mistakes despite prompts
- Getting lost within buildings or parking area currently familiar
- Increasing paranoia, misperceptions, or late‑day agitation
- Limited insight into deficits, paired with resistance to help
If two or more of these are true, memory care is generally the much better fit.
The couple's dilemma
One of the hardest situations involves couples when only one partner has dementia. The majority of assisted living neighborhoods welcome couples and rate the second resident at a reduced rate, including care fees for the partner who requires help. Many memory care systems, by contrast, just allow the person with dementia to live on the secured flooring. A couple of neighborhoods use companion memory care apartments for couples, however not many.
I have actually seen creative options. In one case, a hubby with early Alzheimer's moved to memory look after security, and his partner rented an independent living home in the same structure, investing daylight hours with him and going back to her own bedroom at night. It pleased both security and marital nearness. In another, a couple begun together in assisted living with a clear plan to transition to memory care if he started to exit‑seek. They prioritized distance when exploring and chose a school with both levels of care under one roofing to reduce interruption later.
What to search for when you tour
A building can say it uses dementia care without delivering the details that matter. View the micro‑interactions. Does a caregiver kneel to greet a resident at eye level, or call across the space? Are people engaged in something purposeful, or is the TV bring the load? Are there clear visual cues for the bathroom from the bed? Is the outdoor area genuinely usable, with a flat loop and shade, or is it a locked box no one enters?
Ask pointed concerns. The answers will tell you whether the community's dementia care is a program or a paragraph in a brochure.
- How does staff handle exit‑seeking without physical restraint?
- What is the normal daytime and overnight staffing on the unit?
- What sets off a move to a greater level of care or hospital?
- How are medications managed, and who examines psychotropics?
- Can we do a brief respite stay before signing a longer lease?
If the director can not address, ask to consult with the nurse or memory care coordinator. Transparency today avoids a scramble later.
Money, agreements, and the great print
Care costs seldom relocate a straight line. Anticipate reassessments. If your mother begins requiring two individuals to assist with transfers, or she becomes incontinent, the charge will increase. If she supports, costs rarely return down, though it deserves asking. Take note of move‑in fees, community charges, and whether the structure utilizes a third‑party pharmacy that adds delivery charges. Arbitration stipulations appear in many residency contracts. If you are uneasy with them, ask whether they are optional; in some states they are.
Respite stays can be a wise method to test the fit. A 14 to 30 day trial lets you see how your father does in memory care without dedicating to a year‑long lease. Demand a composed prepare for how personnel will approach his known triggers and choices. If the respite goes well, you acquire confidence. If it does not, you still have your options open.
Long term care insurance coverage can spend for either assisted living or memory care once the policy's criteria are satisfied, usually needing aid with two or more activities of daily living or having a cognitive disability that needs guidance. Start the claim documentation early. Benefits typically start after a removal period of 30 to 90 days.
How timing affects outcomes
Moving too late can produce a high, demanding shift. A person who has actually currently fallen two times or been discovered outside in winter without a coat is arriving with momentum you will need to intercept. The very first two weeks in a brand-new setting are by definition disorienting. Include moving stress to middle phase dementia, and you may see short-lived worsening in habits or confusion. That does not imply the move was incorrect, however it suggests you should not await a crisis to make the decision. I encourage families to tour while the individual with dementia can still walk the halls, satisfy personnel, and take in a few of the brand-new layout. Familiarity, even if partial, assists later.
On the other hand, moving too early can backfire. An avid walker who thrives on long, unsupervised loops around a neighborhood might feel penned in by a protected courtyard, even an excellent one. If insight is still strong and wandering has not emerged, beginning in assisted living and reviewing the strategy every 3 to 6 months may maximize quality of life. There is no universal rule; your loved one's temperament and history matter.
Edge cases that need unique judgment
Young start dementia alters the calculus. A 58‑year‑old with frontal behavioral modifications will not mix well in a memory care unit designed around 80‑plus locals. Try to find neighborhoods with experience in younger locals, more exercise, and staff comfortable with disinhibition and pacing.
Bilingual or bicultural residents are worthy of attention to language and food. Confusion amplifies when the surrounding language is not the one somebody defaulted to in youth. If the only Spanish spoken in the structure is at the reception desk, that will not be enough.
Rural markets can present thin choices. I have helped families who drove 45 minutes to the closest memory care and selected assisted living in your area because they might visit every day. The additional presence compensated for the setting. When you choose between perfect however far and sufficient but near, consider who will appear on Tuesday afternoon in February. Support you can sustain beats a plan you will abandon.
How to prepare the individual and the team
Pack the space like you are building a memory map. Familiar armchair by the window, favorite quilt on the bed, family pictures in consistent locations. Label drawers with words and photos. Bring a small basket of tactile jobs that fit your person's history: playing cards for a previous poker host, large‑piece puzzles for an enthusiast, a tidy box of nuts and bolts for a mechanic. Supply a written life story to the staff. 2 pages are enough. Consist of nicknames, previous careers, foods loved and hated, music that soothes, and subjects to avoid. Good dementia care is personal care.
Stay during the first meals if the community invites it. Watch where your loved one naturally sits and whether staff hint hydration. Bring a trusted routine from home. A brief afternoon walk, a prayer before dinner, or the very same song at bedtime can anchor the day. If there is a bump, resist the reflex to end in 48 hours. Deal with the team. Request a concrete plan to resolve the specific friction point. When households and staff share observations and fine-tune methods, the very first hard week often settles.
Putting the pieces together
Families want a definitive answer to the title concern, however the better goal is a clear choice framework. If threats are contained with predictable triggers, and your loved one can navigate a building securely, assisted living maintains autonomy and typically costs less. If confusion is currently producing roaming, security judgment is jeopardized, or behavior needs specialized methods, a memory care home offers structure that protects dignity by avoiding duplicated failures.
There is space for imagination. Co‑located schools enable a step-by-step move as needs grow. Respite stays let you test without long commitments. Personal responsibility aides can overlay assistance in assisted living to bridge a hard patch, however at an expense. None of these choices lock you in permanently. Dementia care is iterative. You will review the plan as the illness and the individual change.
The families I have seen fare best accept two truths at the same time. Initially, the ideal environment can support function and joy for months or years. Second, dementia continues to advance no matter how great the care is. Your job is not to go after a perfect setting, but to match the setting to the individual you enjoy at this point in time, with eyes open to what follows. When you approach it that way, the labels matter less. Safety, engagement, and respect lead you to the best door.
BeeHive Homes of Henderson provides assisted living care
BeeHive Homes of Henderson provides memory care services
BeeHive Homes of Henderson provides respite care services
BeeHive Homes of Henderson supports assistance with bathing and grooming
BeeHive Homes of Henderson offers private bedrooms with private bathrooms
BeeHive Homes of Henderson provides medication monitoring and documentation
BeeHive Homes of Henderson serves dietitian-approved meals
BeeHive Homes of Henderson provides housekeeping services
BeeHive Homes of Henderson provides laundry services
BeeHive Homes of Henderson offers community dining and social engagement activities
BeeHive Homes of Henderson features life enrichment activities
BeeHive Homes of Henderson supports personal care assistance during meals and daily routines
BeeHive Homes of Henderson promotes frequent physical and mental exercise opportunities
BeeHive Homes of Henderson provides a home-like residential environment
BeeHive Homes of Henderson creates customized care plans as residents’ needs change
BeeHive Homes of Henderson assesses individual resident care needs
BeeHive Homes of Henderson accepts private pay and long-term care insurance
BeeHive Homes of Henderson assists qualified veterans with Aid and Attendance benefits
BeeHive Homes of Henderson encourages meaningful resident-to-staff relationships
BeeHive Homes of Henderson delivers compassionate, attentive senior care focused on dignity and comfort
BeeHive Homes of Henderson has a phone number of (702) 551-0265
BeeHive Homes of Henderson has an address of 1000 Greenway Rd, Henderson, NV 89002
BeeHive Homes of Henderson has a website https://beehivehomes.com/locations/henderson/
BeeHive Homes of Henderson has Google Maps listing https://maps.app.goo.gl/qpZ3TKgbxCu1MVSh8
BeeHive Homes of Henderson has Instagram page https://www.instagram.com/beehivehomeshenderson/
BeeHive Homes of Henderson has an YouTube page https://www.youtube.com/@hamiltonshives4468
BeeHive Homes of Henderson won Top Assisted Living Homes 2025
BeeHive Homes of Henderson earned Best Customer Service Award 2024
BeeHive Homes of Henderson placed 1st for Senior Living Communities 2025
People Also Ask about BeeHive Homes of Henderson
What is BeeHive Homes of Henderson Living monthly room rate?
Our base rate is $4,700 per month for assisted living and $5,700 per month for memory care plus a one-time community fee of $2,500. We do an assessment of each resident's needs prior to move-in, so each resident's rate may be higher. These prices fall into three tiers based on resident needs and range from $4,700/month to $7,300/month. However, after we do the assessment and quote a price, there are no add-ons or hidden fees
Does Medicare and Medicaid pay for a stay at Bee Hive Homes?
Medicare pays for hospital and nursing home stays, but does not pay for assisted living. Some assisted living facilities are Medicaid providers but we are not. We do accept private pay, long-term care insurance, and we can assist qualified Veterans with approval for the Aid and Attendance program
Do we have a nurse on staff?
We do have a nurse on contract who is available as a resource to our staff but our residents' needs do not require a nurse on-site. We always have trained caregivers in the home and awake around the clock
What can you tell me about the food at Bee Hive?
You have to smell it and taste it to believe it! We use dietitian-approved meals with alternates available for flexibility, and we can accommodate needs for different textures and therapeutic diets. We have found that most physicians are happy to relax diet restrictions without any negative effect on our residents
Do we allow pets?
We do allow small pets as long as the resident is able to care for them. State regulations also require that we have evidence of current immunizations for any required shots
Where is BeeHive Homes of Henderson located?
BeeHive Homes of Henderson is conveniently located at 1000 Greenway Rd, Henderson, NV 89002. You can easily find directions on Google Maps or call at (702) 551-0265 Monday through Sunday 9:00am to 5:00pm
How can I contact BeeHive Homes of Henderson?
You can contact BeeHive Homes of Henderson by phone at: (702) 551-0265, visit their website at https://beehivehomes.com/locations/henderson/ or connect on social media via Instagram or Facebook
McCullough Vista Park offers a convenient outdoor setting where families connected with Assisted living memory care senior care elderly care and respite care can enjoy fresh air and meaningful time together.